
Diabetic striatopathy- rare case of Chorea associated with Non-ketotic hyperglycemia
Keywords:
Non-ketotic hyperglycemia, Diabetic striatopathy
Abstract
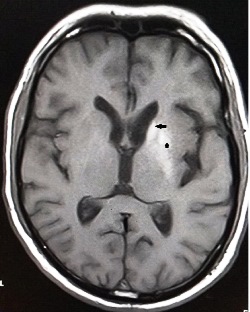
Non-ketotic hyperglycemia (NKHG) has been reported to increase the probability of seizures and movement disorders especially in elderly population. Here we report a case of long standing diabetes who presented with poor glycemic control and choreoathetoid movements of right upper limb, with Magnetic resonance imaging showing hyperintense lesion on T1 sequence in left basal ganglia suggestive of Diabetic striatopathy. These patients may get frequently misdiagnosed to have neurological disease, however recognition of this association is important as the condition may quickly resolve when NKHG is controlled.
Downloads
Download data is not yet available.
References
1. Longo DL, Fauci AS. Harrison’s principles of Internal Medicine. 19th edition. Mc Graw Hill; 2015: 2618-23.
2. Newman RP, Kinkel WR. Paroxysmal choreoathetosis due to hypoglycemia. Arch Neurol 1984; 41:341 – 2.
3. LeeBC, HwangSH, ChangGY. Hemiballismus– hemichorea in older diabetic women: a clinical syndrome with MRI correlation. Neurology 1999; 52:646-8.
4. Lai PH, Tien RD, Chang MH, Teng MM, Yang CF, Pan HB, et al. Chorea-ballismus with nonketotic hyperglycemia in primary diabetes mellitus. AJNR Am J Neuroradiol 1996; 17(6): 1057-64.
5. Faundez T, Klee P, Hanquinet S, et al. Diabetic striatopathy in childhood. A case report. Pediatrics 2016; 137.
6. Nabatame H, Nakamura K, Matsuda M, Fujimoto N, Shio H. Hemi- chorea in hyperglycemia associated with increased blood flow in the contralateral striatum and thalamus. Int Med 1994;33:472 – 5.
7. Shan DE, Ho DM, Chang C, Pan HC, Teng MM. Hemichorea – hemi- ballism: an explanation for MR signal changes. Am J Neuroradiol 1998;19:863 – 70.
8. Postuma RB, Lang AE. Hemiballism: revisiting a classic disorder. Lancet Neurol 2003; 2(11): 661-8.
9. El Otmani H, Moutaouakil F, Fadel H, El Ouafi N, Abdoh Rafai M, El Moutaouakil B, et al. Chorea-ballismus in acute non- ketotic hyperglycaemia. Funct Neurol 2009; 24(3): 129-32.
10. Ohara S, Nakagawa S, Tabata K, Hashimoto T. Hemiballism with hyperglycemia and striatal T1-MRI hyperintensity: an autopsy report. Mov Disord 2001; 16(3): 521-5.
11. Guisado R, Arieff AI. Neurological manifestations of diabetic comas: correlation with biochemical alterations in the brain. Metabolism 1975;24:665 – 79.
12. S.H. Oh et al. Chorea associated with non-ketotic hyperglycemia and hyperintensity basal ganglia lesion on T1-weighted brain MRI study: a meta-analysis of 53 cases including four present cases Journal of the Neurological Sciences 200 (2002) 57–62
13. Krieger D, Krieger S, Jansen O, Gass P, Theilmann L, Lichtnecker H. Manganese and chronic hepatic encephalopathy. Lancet 1995;346: 270–4.
14. Fujioka M, Sakaki T, Hiramatsu K, Miyamoto S, Iwasaki S. Specific changes in human brain following reperfusion after cardiac arrest. Stroke 1994;25:2091-5.
15. Fujioka M, Hiramatsu K, Sakaki T, Sakaguchi S, Ishii Y. Specific changes in human brain after hypoglycemic injury. Stroke 1997;28: 584–7.
16. Mirowitz SA, Westrich T, Hirsh JD. Hyperintense basal ganglia on T1-weighted MR images in patients receiving parental nutrition. Ra- diology 1991;181:117 – 20.
17. Younes S, Cherif Y, Seizures and movement disorders induced by hyperglycemia without ketosis in elderly. Iran J Neurol 2014; 13(3).
18. Scherer C. Seizures and non-ketotic hyperglycemia. Presse Med 2005; 34(15): 1084-6. [In French].
19. Lammouchi T, Zoghlami F, Ben SL, Grira 12. M, Harzallah MS, Benammou S. Epileptic seizures in non-ketotic hyperglycemia. Neurophysiol Clin 2004; 34(3-4): 183-7. [In French].
20. Hennis A, Corbin D, Fraser H. Focal 16. seizures and non-ketotic hyperglycaemia. J Neurol Neurosurg Psychiatry 1992; 55(3): 195-7.
Published
2019-12-10
How to Cite
1.
Bhat MH, Sidana S, Masoodi SR, Sharma A. Diabetic striatopathy- rare case of Chorea associated with Non-ketotic hyperglycemia. jms [Internet]. 2019Dec.10 [cited 2026Oct.2];22(2):42-4. Available from: https://www.jmsskims.org/index.php/jms/article/view/483
Section
Case Reports

This work is licensed under a Creative Commons Attribution 4.0 International License.


